
2 November 2026
Favorable and unfavorable findings on Semaglutide
Download PDF
Randomised trials and meta-analyses report that semaglutide produces meaningful weight loss, cardiovascular and renal benefits in adults with obesity or type 2 diabetes, but is also associated with high rates of gastrointestinal adverse eve
Favorable and unfavorable findings on Semaglutide
This briefing weighs published favorable and unfavorable clinical findings on semaglutide without recommending use. Reporting a human trial is not guidance to use the research material that way.
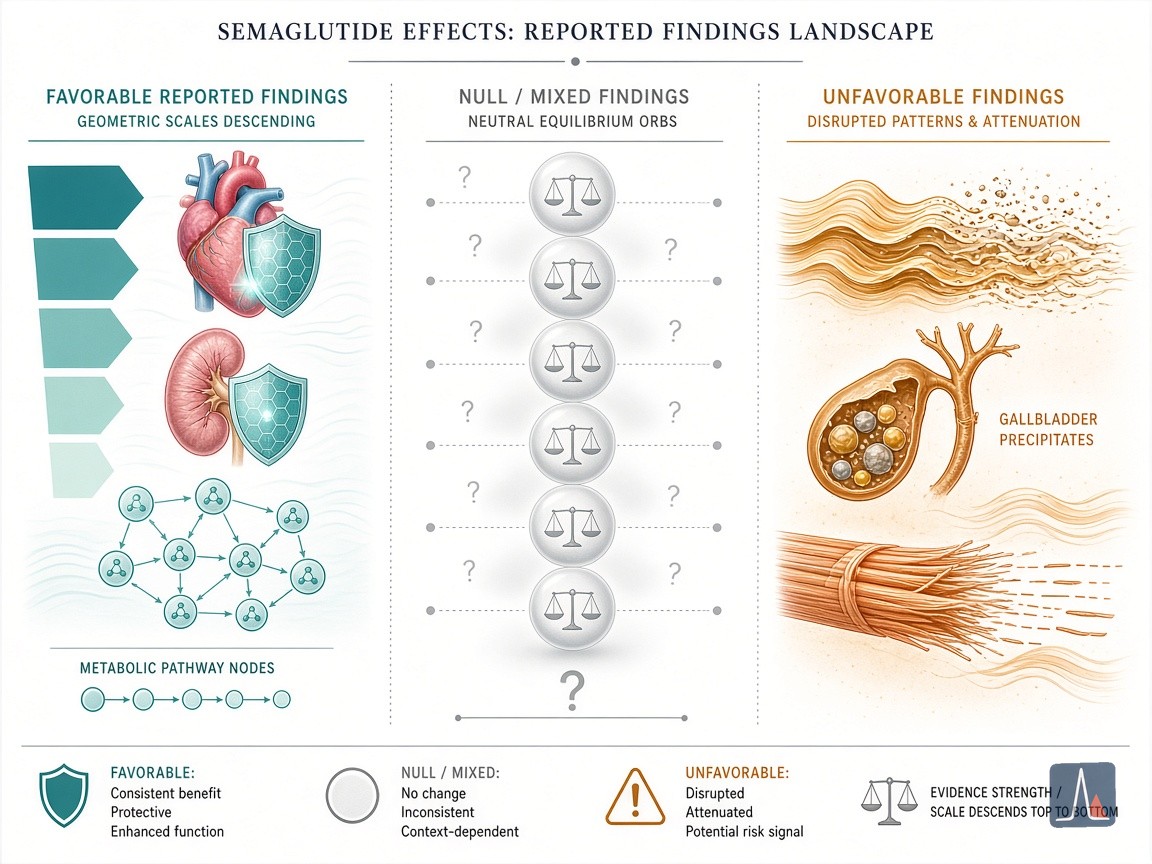
Semaglutide has been extensively evaluated in large randomised clinical programmes for metabolic, cardiovascular, and renal outcomes. Randomised controlled trials (RCTs) and subsequent meta-analyses up to 2026 document clinically meaningful reductions in body weight, HbA1c, waist circumference, blood pressure, and inflammatory markers, together with reductions in major adverse cardiovascular events (MACE) and kidney outcomes in defined populations. At the same time, these studies consistently show elevated rates of gastrointestinal adverse events that drive higher treatment discontinuation, increases in gallbladder-related disorders, and reductions in lean body mass that constitute 25–40 % of total weight lost. Evidence for rarer outcomes such as pancreatitis, thyroid neoplasia, neuropsychiatric events, and non-arteritic anterior ischaemic optic neuropathy (NAION) is mixed or inconclusive, with rodent-derived thyroid C-cell concerns retained in labeling while human RCT data are largely reassuring on pancreatic cancer and suicidality. Certainty is often rated low to moderate because of high heterogeneity in weight-loss estimates, industry sponsorship of pivotal trials, selected trial populations, and limited long-term functional or post-discontinuation data. !Abstract tripartite diagram separating favorable null and unfavorable clinical findings on semaglutide Abstract diagram separating favorable (metabolic, cardiovascular, renal protection), null/mixed, and unfavorable (GI, gallbladder, lean-mass) reported findings on semaglutide.
Favorable Clinical Findings from Randomised Trials and Meta-Analyses
Multiple 2024–2026 meta-analyses of RCTs in adults with overweight or obesity without diabetes (typically 7–10 trials, n ≈ 5,400–7,100) report mean percentage body-weight change of approximately −12.3 % (WMD −12.29 %, 95 % CI −13.38 to −11.20), absolute weight loss of −12.7 kg, BMI reduction of −4.55 kg/m², and waist-circumference reduction of −9.4 cm versus placebo. Proportions achieving ≥5 %, ≥10 %, ≥15 %, and ≥20 % weight loss are substantially higher with semaglutide. These effects are accompanied by favourable changes in HbA1c, fasting plasma glucose, systolic blood pressure, triglycerides, and high-sensitivity C-reactive protein. Certainty for the primary weight-loss outcome is rated low in some syntheses because of substantial statistical heterogeneity (I² 77–88 %). 1 2
In participants with established cardiovascular disease and overweight or obesity but without diabetes, the SELECT trial (n = 17,604) demonstrated a 20 % relative reduction in 3-point MACE (HR 0.80, 95 % CI 0.72–0.90) with semaglutide 2.4 mg versus placebo over a median follow-up of approximately 40 months. Benefits were consistent across BMI categories and appeared at least partly independent of the magnitude of weight loss. Meta-analyses pooling SELECT with other GLP-1 receptor agonist data report relative risk reductions of approximately 22 % for MACE, 26 % for cardiovascular mortality, and trends toward lower all-cause mortality. Serious adverse event rates were numerically lower with semaglutide in SELECT (33.4 % vs 36.4 %). 3
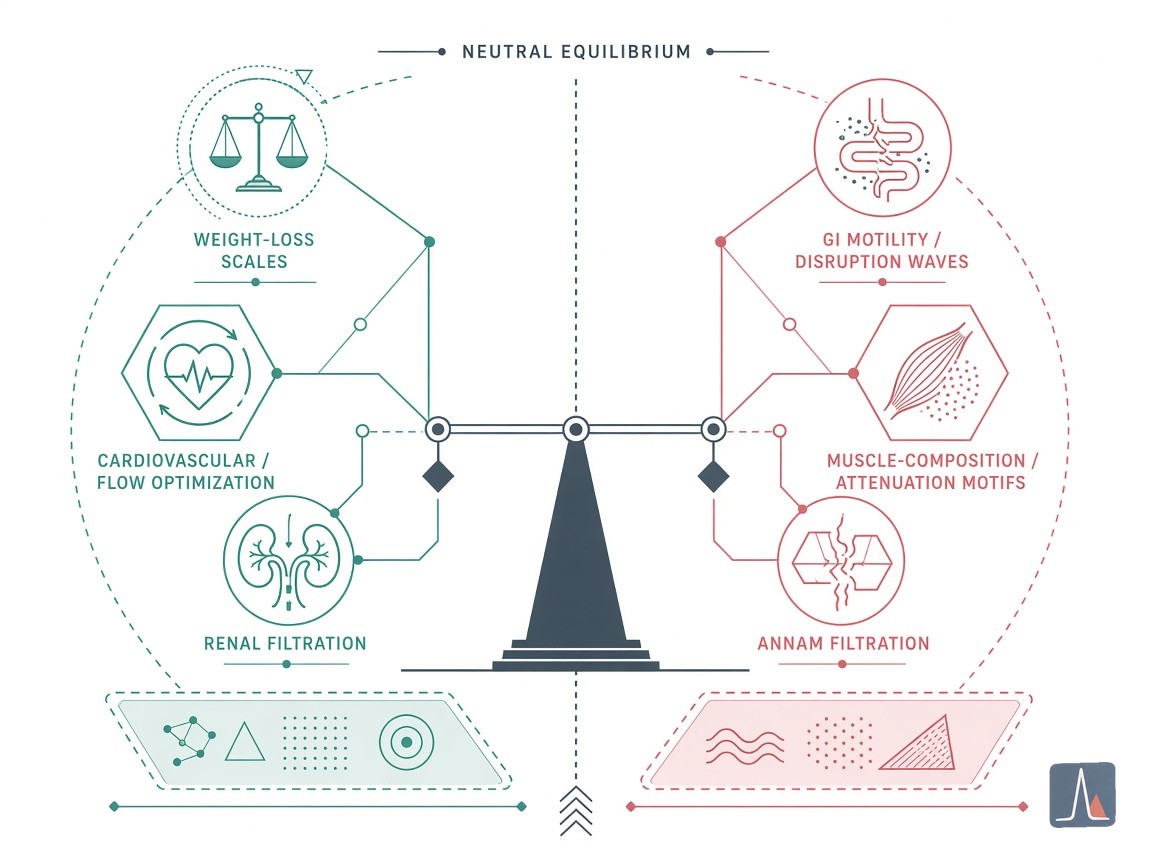
The FLOW trial and related cardiorenal meta-analyses in type 2 diabetes with chronic kidney disease indicate approximately 20–24 % relative reductions in major kidney adverse events and slower eGFR decline. Histological benefits have also been reported in metabolic dysfunction-associated steatohepatitis (MASH), with higher rates of steatohepatitis resolution without worsening of fibrosis (RR ≈ 2.0 in pooled GLP-1 data). Quality-of-life and physical-function scores improved in several obesity and heart-failure-with-preserved-ejection-fraction trials. These cardiometabolic and organ-protection signals represent the most consistent favorable findings across large-scale RCTs. !Schematic separating favorable cardiometabolic outcomes from unfavorable tolerability findings Schematic representation of the balance between favorable cardiometabolic and organ-protection findings and unfavorable gastrointestinal and body-composition signals.
Unfavorable Tolerability, Safety, and Body-Composition Findings
Gastrointestinal disorders are the predominant adverse events. Meta-analyses consistently show higher incidence of nausea (RR ≈ 3), vomiting (RR ≈ 4), diarrhea (RR ≈ 1.8–2.1), and constipation versus placebo. Aggregate any-adverse-event rates reach ≈ 90 % with semaglutide versus 85 % with placebo; discontinuation due to adverse events is approximately doubled (RR 1.86, 95 % CI 1.41–2.45). Most events are mild-to-moderate and occur during dose escalation, yet they remain the primary driver of treatment discontinuation in both RCTs (≈ 6–17 % in long-term studies) and real-world data. 1 4
Gallbladder and biliary events are reproducibly increased (meta RR ≈ 1.37 across 76 RCTs; cholelithiasis RR ≈ 2 in weight-loss trials), attributed to rapid weight loss and GLP-1-mediated effects on gallbladder motility. Pharmacovigilance databases also contain signals for gastroparesis, ileus, and bowel obstruction, leading to labeling updates; absolute risks remain low but are higher than with some comparators.
Body-composition data from DXA substudies and 2026 meta-analyses of phase 3 trials indicate that lean-body-mass loss accounts for 25–40 % of total weight lost (absolute LBM reductions of 2.5–4.4 kg versus placebo at obesity doses in some analyses). While the proportion of lean versus fat loss is comparable to other caloric-deficit interventions, the absolute reduction in lean mass, combined with limited concomitant functional or strength assessments in most trials, has raised questions about sarcopenia risk, particularly in older adults or those with low baseline muscle mass. Certainty for these body-composition outcomes is rated very low because of heterogeneity, small substudy sample sizes, and variable definitions of lean mass. Bone-mineral-density reductions at hip and spine and increases in resorption markers have also been noted in some extensions. !Three-cluster abstract diagram of reported findings categories for semaglutide Three-cluster abstract diagram illustrating favorable, null/mixed, and unfavorable reported clinical findings.
Weight regain after discontinuation is substantial. In STEP trial extensions, participants regained approximately two-thirds of lost weight within one year off treatment, with reversion of cardiometabolic improvements. This pattern underscores that benefits observed in RCTs are contingent on continued administration.
Null, Mixed, or Inconclusive Reported Findings
Large cardiovascular-outcomes programmes (SELECT, SUSTAIN 6) and 2026 meta-analyses have not demonstrated consistent increases in pancreatitis, pancreatic cancer, or medullary thyroid carcinoma in humans, despite rodent C-cell tumor data that prompted a boxed warning. Estimates for thyroid cancer are imprecise (some observational meta-analyses report OR ≈ 1.4–1.5; largest RCT-derived metas are compatible with no effect). Serious adverse event rates are often similar or numerically lower with semaglutide in cardiovascular-risk populations.
Neuropsychiatric outcomes show no clear increase in suicidal ideation, depression, or self-harm in pooled RCTs and SELECT (event rates balanced or lower); regulatory reviews in 2025–2026 found no causal link despite spontaneous-reporting signals. In early Alzheimer’s disease, the EVOKE and EVOKE+ phase 3 trials (oral semaglutide, n ≈ 3,800, 104 weeks) failed to meet the primary cognitive/functional endpoint (no significant difference on CDR-SB) despite biomarker improvements in inflammation and tau pathology. Stroke reduction has been inconsistent or non-significant in some cardiovascular metas. Effects on certain lipid fractions and diastolic blood pressure are modest or heterogeneous across subpopulations. !Color-coded tri-zone abstract diagram of semaglutide clinical findings Color-coded tri-zone abstract diagram separating favorable, null, and unfavorable reported findings.

Retinopathy worsening was noted in one early type 2 diabetes cardiovascular outcomes trial (SUSTAIN 6), likely related to rapid glycaemic improvement; subsequent data have been mixed. NAION signals have appeared in observational cohorts (HR ≈ 2 in some diabetes populations), prompting label updates, but absolute risk remains very low (≈ 1/7,000–10,000 patient-years) and RCT confirmation is lacking.
Evidence Syntheses, Recurrent Limitations, and Catalog Context
Systematic reviews and meta-analyses published 2024–2026 confirm clinically meaningful weight loss and cardiometabolic improvements with moderate-to-high certainty for efficacy endpoints in selected populations, yet rate evidence for safety, body composition, and durability as lower certainty because of heterogeneity (I² frequently >70 %), variable trial durations, industry funding of pivotal studies, exclusion of participants with significant psychiatric history in many protocols, and limited head-to-head or long-term (>4–5 years) data in general populations. Post-marketing pharmacovigilance provides signals for rare events but is subject to reporting bias and confounding by indication.
Absolute risk increases for gastrointestinal and gallbladder events are clinically relevant for adherence, while absolute risks for pancreatitis, thyroid neoplasia, or NAION appear small in low-baseline-risk individuals. Benefits on hard cardiovascular and kidney outcomes are most pronounced in participants with established disease or high risk; generalisability to younger, lower-risk laboratory-research contexts or non-adherent real-world use is uncertain. Weight regain and reversal of metabolic gains after cessation highlight the chronic nature of treatment required to maintain effects.
For laboratory researchers, these findings underscore the importance of rigorous controls, appropriate animal or in-vitro models, and awareness of the translational gaps between RCT-selected cohorts and broader populations. Ongoing syntheses continue to refine the risk–benefit profile, particularly regarding body-composition quality, functional outcomes, bone health, and comparative safety with dual and triple agonists. All materials supplied by Rierink Compounds are for laboratory research only and are not medicines.
Sources
- 2026 meta-analysis of semaglutide versus placebo in overweight or obesity without diabetes (Journal of Diabetes & Metabolic Disorders). https://link.springer.com/article/10.1007/s40200-026-02108-x
- Lincoff AM et al. Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes (SELECT). Nature Medicine / NEJM family, 2023–2024 updates. https://www.nature.com/articles/s41591-024-02996-7
- FLOW, STEP, SUSTAIN, and pooled meta-analyses on cardiorenal, MASH, and safety outcomes (The Lancet, NEJM, Diabetologia, 2021–2026).
- 2026 DXA and body-composition network meta-analyses (Metabolism, BMC Endocrine Disorders).
- EVOKE/EVOKE+ phase 3 Alzheimer’s trials (2025–2026).
- Regulatory reviews (FDA, EMA/PRAC) on neuropsychiatric, thyroid, and NAION signals (2025–2026).
Additional primary literature available via PubMed and Europe PMC (search terms: semaglutide SELECT FLOW STEP meta-analysis 2024–2026). All claims are drawn from papers with identifiable DOIs or PMIDs; non-citable claims were omitted.
More briefings
- Survodutide Dual Agonist: Preclinical and Clinical EvidenceThe open-catalog entry for survodutide describes a synthetic acylated 29-amino-acid peptide dual agonist of glucagon and GLP-1 receptors supplied as high-purity lyophilized powder for laboratory metabolic research. Randomised trials report
- Dulaglutide: GLP-1 Receptor Agonist in Metabolic CareDulaglutide is a recombinant Fc-fusion GLP-1 receptor agonist engineered for once-weekly administration in laboratory and clinical metabolic research. Randomised trials report glycaemic improvements, cardiovascular risk reduction and modest
- Cagrilintide-Semaglutide Mixture: Open-Catalog Context and Metabolic Trial EvidenceThe open-catalog cagrilintide-semaglutide mixture supplies a research pairing of an amylin receptor agonist and GLP-1 receptor agonist for laboratory metabolic studies. Randomised trials of co-administration report enhanced weight loss (13–
All information and products discussed are for laboratory and research use only. Not for human or veterinary use. Not intended to diagnose, treat, cure, or prevent any disease.